

- OBGYNTEAM
Placenta Accreta Specialist in New Jersey
If You Were Just Told You May Have Placenta Accreta, Start Here
If you were recently told that you may have placenta accreta, you are probably frightened.

- You may be asking
01
Is my baby going to be okay?
02
How serious is this?
03
Will I need a hysterectomy?
04
Could I lose my uterus?
05
Is there any way to preserve my fertility?
06
Where should I deliver?
07
Do I need another opinion?
08
Who is experienced enough to take care of me?
These are not small questions.
And you should not be expected to figure everything out by yourself.
At OBGYNTEAM, we evaluate women with suspected or confirmed placenta accreta spectrum (PAS) and help develop an individualized plan for pregnancy, delivery, and treatment.
- Our approach is straightforward
01
Understand exactly what is happening.
02
Explain what it means.
03
Discuss the safest options.
04
Plan carefully.
05
Make sure you know what comes next.
What Is Placenta Accreta Spectrum?
Placenta accreta spectrum describes a range of conditions in which the placenta attaches too deeply to the uterus.
- The spectrum includes

01
Placenta accreta
the placenta attaches abnormally deeply to the uterine wall.

02
Placenta increta
the placenta grows more deeply into the uterine muscle.

03
Placenta percreta
the placenta grows through the uterine wall and may involve nearby organs.
Placenta accreta can cause severe bleeding during delivery, which is why recognizing the condition before delivery and planning appropriately are so important.
But one of the most important things to understand is this:
A diagnosis of placenta accreta does not mean that every woman has the same condition or needs exactly the same conversation.
The location of the placenta, the depth and extent of placental invasion, your previous surgeries, the number of prior C-sections, your overall health, your pregnancy, and your future fertility goals all matter.
Placenta Accreta After a C-Section: Why Your History Matters
A previous C-section is one of the most important risk factors for placenta accreta spectrum, and the risk increases as the number of previous C-sections increases.
The combination of placenta previa and a previous C-section is particularly important.
That does not mean that every woman with a prior C-section and placenta previa has placenta accreta.
It means that the possibility needs to be evaluated carefully.
Your individual history matters.
We look at:
This is why we do not want you to make decisions based on a diagnosis written on a report alone.
We want to understand the entire picture.
- Number of previous C-sections
- Location of the placenta
- Whether placenta previa is present
- Previous uterine surgery
- Prior placenta or pregnancy complications
- Ultrasound findings
- Symptoms and clinical history
- The relationship between the placenta and previous uterine scars
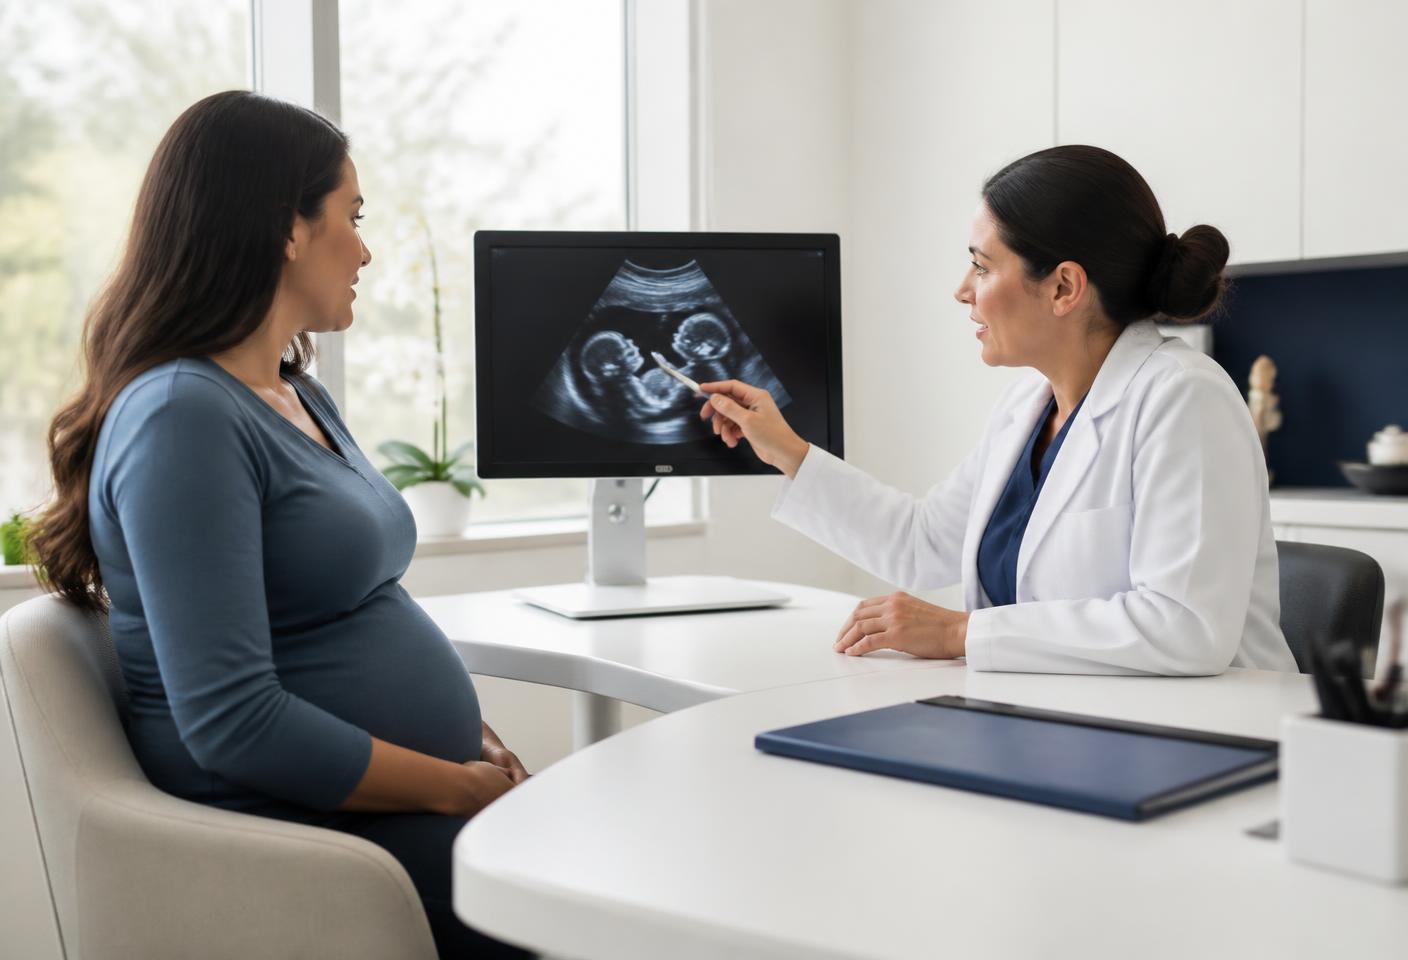
How Is Placenta Accreta Diagnosed?
Detailed Placental Ultrasound
Ultrasound is an important part of evaluating suspected placenta accreta.
The goal is not simply to determine where the placenta is located. The examination looks for findings that may suggest abnormal placental attachment and evaluates the relationship between the placenta and the uterus.
Importantly, a normal or inconclusive ultrasound does not always completely exclude placenta accreta.
Your clinical risk factors and surgical history still matter.
Review of Your Previous Imaging and Medical Records
If you have already had an ultrasound, MRI, consultation, or previous surgical evaluation, bring those records with you.
We can review:
- Ultrasound images and reports
- MRI when performed
- Previous C-section operative reports
- Previous uterine surgery
- Placental location
- Prior pregnancy records
- Recommendations you have already received
Our goal is to answer an important question:
What do we actually know about your placenta—and what still needs to be clarified?
What Happens When You Come to Us?
For many patients with confirmed placenta accreta spectrum, the generally accepted approach is cesarean hysterectomy with the placenta left in place after delivery of the baby.
Attempting to forcibly remove an abnormally adherent placenta can cause severe hemorrhage.
That is why placenta accreta should never be treated like a routine C-section.
But understanding the standard treatment does not mean that every patient has an identical situation.
There are carefully selected circumstances in which conservative or expectant management may be considered.
01
What are we concerned about?
We will explain what your imaging and history suggest.
02
What still needs to be evaluated?
Sometimes the diagnosis is suspected but not yet certain. Additional imaging, specialist review, or further evaluation may be appropriate.
03
How serious does this appear to be?
Placenta accreta exists on a spectrum. Understanding the suspected location and extent of placental involvement helps guide planning.
04
Where should delivery take place?
For significant or confirmed placenta accreta spectrum, delivery planning should involve a hospital and team prepared for complex obstetric surgery and potentially major hemorrhage.
05
Who needs to be involved?
Depending on the individual case, planning may involve maternal-fetal medicine, experienced obstetric surgeons, anesthesia, blood-bank resources, neonatology, urology, interventional radiology, or other surgical specialists.
06
What are the treatment options?
This is where your individual anatomy, medical situation, and goals become especially important.
Placenta Accreta Treatment: What Are My Options?
For many patients with confirmed placenta accreta spectrum, the generally accepted approach is cesarean hysterectomy with the placenta left in place after delivery of the baby. Attempting to forcibly remove an abnormally adherent placenta can cause severe hemorrhage. That is why placenta accreta should never be treated like a routine C-section. But understanding the standard treatment does not mean that every patient has an identical situation.
There are carefully selected circumstances in which conservative or expectant management may be considered.

The question is not:
“Can we promise that you will keep your uterus?”
The right question is:
“What is the safest approach for you, and is preserving your uterus a reasonable possibility in your particular situation?”
That distinction matters.
Will I Need a Hysterectomy?
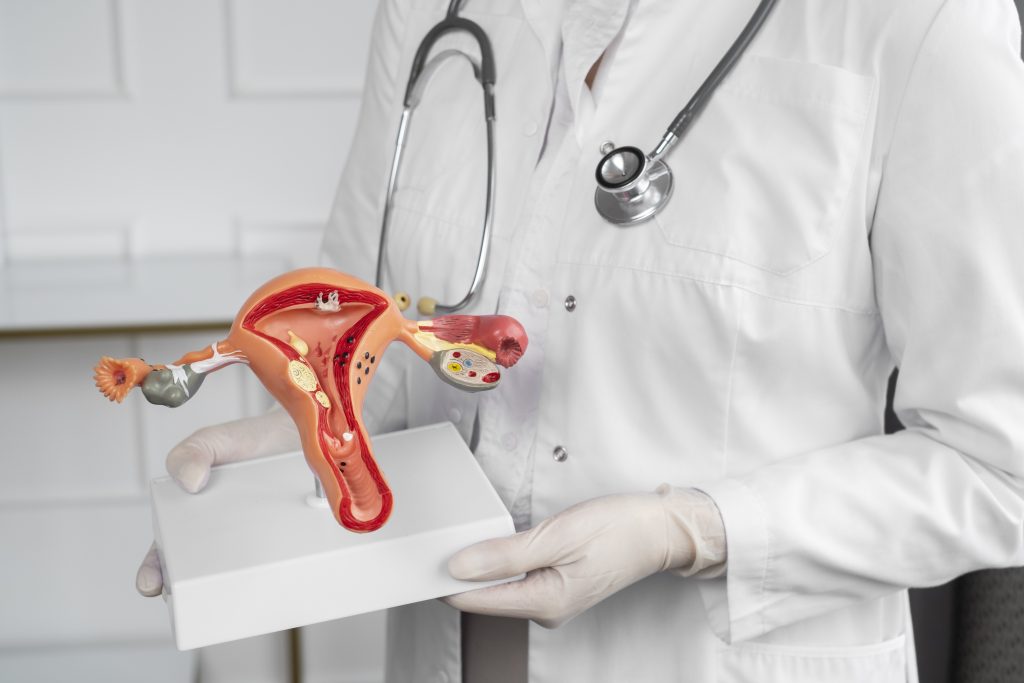
Maybe, but it depends on your individual situation.
For many women with confirmed placenta accreta spectrum, cesarean hysterectomy remains the most established approach for reducing the danger associated with attempting placental separation.
We will never tell you that a hysterectomy is insignificant.
For some women, it is emotionally devastating because it means the end of future childbearing.
For others, the priority is making the safest possible decision for mother and baby.
Your goals deserve to be part of the conversation from the beginning.
If preserving your uterus and future fertility are important to you, tell us.
Can My Uterus Be Preserved?
Uterus-Preserving Treatment Is Not Right for Everyone
In carefully selected patients, conservative or expectant approaches may sometimes be considered.
These approaches are different from simply “removing the placenta.”
Depending on the individual situation, management may involve removing the placenta and affected tissue while leaving the uterus in place, or leaving some or all of the placenta in situ.
These approaches can carry significant risks, including:
01
Severe or delayed bleeding
02
Infection
03
Need for additional surgery
04
Delayed hysterectomy
05
Blood transfusion
06
Serious maternal complications
For that reason, uterus-preserving management requires careful patient selection, detailed counseling, appropriate expertise, and appropriate hospital resources.
We will not promise you that your uterus can be saved.
We will evaluate whether preserving it is medically reasonable and explain the potential benefits, risks, uncertainties, and alternatives.
That is a very different conversation from simply being told:
“You need a hysterectomy.”

If You Want More Children, We Want to Know
If future pregnancy matters to you, tell us before a treatment plan is finalized.
Your desire for future fertility does not override safety, but it absolutely belongs in the medical discussion.
We can discuss:
- Whether uterine preservation is medically reasonable
- The risks of conservative or expectant management
- The possibility that hysterectomy could ultimately still be necessary
- What future pregnancy may mean after uterine-preserving treatment
- The uncertainties associated with fertility-preserving approaches
You deserve to understand the implications before making an important decision.
You Don't Have to Decide Everything at Your First Visit
Being told you may have placenta accreta can make it feel as though you need to make every decision immediately.
You don't.
Our first step is to understand your pregnancy, review your imaging and previous surgeries, and determine what we are actually dealing with.
Then we can talk about the options.
If hysterectomy is the safest approach, we will explain why.
If uterine preservation may be reasonable in your situation, we will explain that too, including the risks and limitations.
You should never feel pressured to agree to a treatment you do not understand.
Planning Your Delivery
Placenta accreta is not a condition that should be managed casually or at the last minute.
ACOG and SMFM emphasize antenatal diagnosis, planned delivery, experienced multidisciplinary care, appropriate hospital resources, and preparation for potentially severe hemorrhage.
Your delivery plan may involve coordination with:

High-risk obstetrics

Maternal-fetal medicine

Experienced obstetric surgeons

Anesthesiology

Blood-bank and transfusion services

Neonatology

Urology

Interventional radiology

Other surgical specialists when appropriate
The exact team depends on your individual diagnosis.
Good placenta accreta care is not simply about having a skilled surgeon. It is about having the right plan before the emergency occurs.
- A Different Kind of High-Risk Care
Expertise Matters. So Does How You Are Treated.
Large medical centers can offer tremendous resources and highly specialized teams.
But when you are facing a frightening diagnosis, you also need someone who will slow down enough to explain what is happening.
At OBGYNTEAM, our goal is to combine complex obstetric and surgical experience with individualized, physician-led care.
We want you to understand:
- What your imaging shows
- What your risks are
- What treatment may be recommended
- Why that treatment may be recommended
- Whether there are reasonable alternatives
- What your future fertility may mean for the discussion
- Where your delivery should occur
- What happens next

You should not feel like a diagnosis moving through a large system.
You should feel like a patient whose individual situation has been carefully understood.
Our Approach to Complex Placenta Cases

We Know the Standard Treatment
We respect established medical guidelines and the importance of delivering patients with significant placenta accreta spectrum at appropriately equipped hospitals with experienced teams.

We Also Know That Patients Are Individuals
The safest treatment for one woman may not be the same as the safest treatment for another.
Your anatomy, placental location, previous C-sections, surgical history, medical condition, and reproductive goals all matter.

We Plan Before There Is a Crisis
The purpose of evaluation is not simply to give you a diagnosis.
It is to create a plan.
A good plan anticipates:
- Where delivery should occur
- What surgery may be necessary
- What your anesthesia needs may be
- What happens if the surgical findings are different from what imaging predicted
- Who should be involved
- How hemorrhage will be managed
- What your baby's needs may be
The more we understand before delivery, the more prepared we can be.
If You Were Told You Have Placenta Accreta, You Can Get a Second Opinion
You may already have been told:
“You have placenta accreta and will need a hysterectomy.”
You may be wondering whether that is the only option.

A second opinion can help you understand:
- Whether the diagnosis appears accurate
- How extensive the suspected placental invasion may be
- Whether additional imaging or specialist evaluation would be helpful
- Why a particular treatment has been recommended
- Whether uterine preservation is medically reasonable to discuss
- Where delivery should take place
- What questions you should ask your surgical team
You do not need to know exactly what you are looking for before you come.
Bring us the diagnosis, your imaging, and your questions. We will help you understand the situation.
You May Be Looking for Someone Who Understands How Scary This Is We do.
- You may be worried about your baby.
- You may be worried about severe bleeding.
- You may be worried about surgery.
- You may be worried about losing your uterus.
- You may simply be overwhelmed because someone gave you a serious diagnosis without explaining what happens next.
Our approach is to slow the process down enough to make it understandable.
01
We listen.
02
We evaluate.
03
We explain.
04
We plan.
And when there are medically reasonable options, we discuss them with you rather than assuming that one treatment fits every woman.
Placenta Accreta Care for Women Throughout Northern New Jersey and Rockland County
Women seeking evaluation for suspected placenta accreta come from throughout Northern New Jersey and the surrounding New York region, including:
Paramus Office
Clifton Office
OBGYNTEAM has offices in Paramus and Clifton, New Jersey, providing access to specialized obstetric evaluation for women who may be facing complex placental conditions.
If you have been referred from another OB-GYN, maternal-fetal medicine specialist, ultrasound center, or hospital, we can review the information you already have and help determine the next step.
You Don't Have to Navigate This Alone
A placenta accreta diagnosis can make pregnancy feel suddenly uncertain.

- But uncertainty isn't the same as having no plan.
- The first step is understanding exactly what is happening.
- The next step is determining what care is safest.
- And then we plan carefully with you, your baby, your medical history, and your goals in mind.
- If you were recently told you may have placenta accreta, placenta increta, placenta percreta, or placenta previa with a previous C-section, we invite you to schedule a consultation.
Frequently Asked Questions About Placenta Accreta
Is placenta accreta dangerous?
Placenta accreta spectrum can cause severe bleeding and other serious complications during delivery. The risk is one reason antenatal diagnosis and delivery planning are so important.
Does placenta previa mean I have placenta accreta?
No. Placenta previa does not automatically mean you have placenta accreta. However, placenta previa combined with previous C-sections substantially increases concern for placenta accreta spectrum and warrants careful evaluation.
Does having multiple C-sections increase the risk of placenta accreta?
Yes. Previous cesarean delivery is an important risk factor, and the risk increases with the number of previous C- sections.
Can ultrasound diagnose placenta accreta?
Ultrasound is an important diagnostic tool, but no single ultrasound finding should be interpreted in isolation. Your clinical history and risk factors are also important.
Will I definitely need a hysterectomy if I have placenta accreta?
No individual diagnosis can answer that question without evaluating the specific circumstances. For many confirmed cases, cesarean hysterectomy with the placenta left in place is the generally accepted approach. Carefully selected patients may sometimes be considered for uterus-preserving management.
Can placenta accreta be treated without removing the uterus?
In selected cases, conservative or expectant management may be considered. These approaches are not appropriate for everyone and can involve significant risks, including severe bleeding, infection, delayed complications, and eventual hysterectomy.
Can I preserve my fertility after placenta accreta?
Possibly, depending on the individual circumstances. If future fertility is important to you, tell your physician before treatment decisions are finalized so that fertility considerations can be incorporated into the discussion.
Should I get a second opinion for placenta accreta?
A second opinion may be helpful, particularly when you have been given a diagnosis or treatment recommendation that you do not fully understand or when future fertility is an important concern.
Where should I deliver if I have placenta accreta?
Patients with significant or confirmed placenta accreta spectrum generally require delivery planning at a hospital equipped for complex obstetric surgery, severe hemorrhage, blood transfusion, and multidisciplinary care.
What should I bring to my placenta accreta consultation?
Bring your ultrasound reports and images if available, MRI reports or images if performed, prior C-section operative reports, other uterine surgery records, and recommendations from your current physicians.
Trusted Medical Resources
We encourage patients to learn from reputable medical organizations, including the American College of Obstetricians and Gynecologists, the Society for Maternal-Fetal Medicine, and the Royal College of Obstetricians and Gynecologists.